You clicked on “Pelvic Pain in Women? Gynecologist on Endometriosis, Fibroids” because you want clear answers. Pelvic pain has many causes, and one visit can change your plan for months ahead. In this guide, we unpack the three common culprits behind chronic pelvic pain—endometriosis, fibroids, and adenomyosis—so you understand symptoms, tests, and modern treatments that support pain relief and future fertility.
Pelvic pain deserves a closer, calmer look
Pelvic pain ranges from dull cramps to sharp, cycle-linked pain. Sometimes it is brief. However, persistent or worsening pain needs attention. The goal is not only to rule out emergencies but also to find a root cause you can treat.
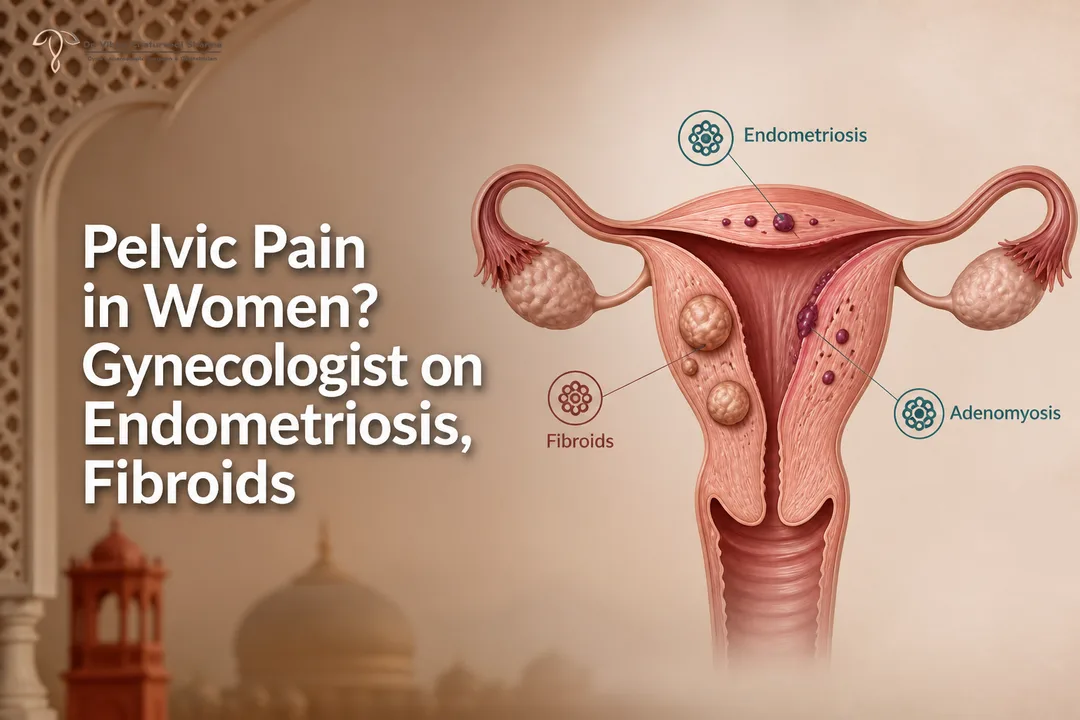
At our Jaipur practice, we often see patterns. For instance, severe period pain that keeps you from work may hint at endometriosis. Meanwhile, pressure or a feeling of pelvic fullness may point toward fibroids. Importantly, heavy bleeding with a boggy, enlarged uterus can suggest adenomyosis. Each condition behaves differently, so the right roadmap begins with the right label.
- Seek urgent care for fever, fainting, positive pregnancy with pain, or sudden one-sided pain.
- See a specialist soon if pain disrupts school, work, sex, or sleep.
- Track your cycle, flow volume, and pain location before the visit.
How a Gynecologist pinpoints the cause
A thorough history starts the puzzle. Next, a focused exam checks tenderness, uterine size, and mobility. Then, imaging and selected labs narrow the field. Ultrasound is the first-line tool because it is quick, affordable, and highly informative. MRI helps in tricky cases, especially for adenomyosis or deep infiltrating endometriosis. Finally, we match findings with your goals, such as pain control, fertility, or period management.
Endometriosis: hallmark signs and diagnostic steps
Endometriosis happens when tissue like the uterine lining grows outside the uterus, often on ovaries, ligaments, or the peritoneum. Classic clues include severe period pain, pain with intercourse, and bowel or bladder pain around menses. According to the World Health Organization, it affects about 10% of reproductive-age women worldwide, which explains why we see it frequently in clinic. Ultrasound can detect ovarian endometriomas. However, many implants remain invisible on scans, so we correlate symptoms and exam closely.
Medical therapy often comes first. Nonsteroidal anti-inflammatories help pain. In addition, hormonal options such as combined pills, progestins, or a levonorgestrel IUD can suppress the disease’s activity. Some patients also benefit from GnRH analogues for short periods under supervision. Meanwhile, pelvic physiotherapy and pain education reduce central sensitization, which amplifies pain signals over time.
Laparoscopy: what to expect
When symptoms persist or fertility is a top priority, we discuss diagnostic laparoscopy. Through tiny keyhole incisions, we inspect the pelvis and remove visible lesions. Most patients go home the same day and resume light activity within a few days. As always, recovery time and results vary with disease severity and the extent of surgery.
Fibroids: pressure, bleeding, and imaging
Fibroids are benign muscle tumors of the uterus. They can cause heavy bleeding, clots, anemia, pelvic pressure, constipation, and frequent urination. Many grow with estrogen exposure. Notably, the American College of Obstetricians and Gynecologists reports that most women develop fibroids by age 50. Ultrasound usually confirms the diagnosis and shows size, number, and location—submucosal (inside the cavity), intramural (within the wall), or subserosal (on the outside).
Treatment depends on your symptoms and life plans. For heavy bleeding, we start with medicines such as tranexamic acid during menses or hormonal therapy to thin the lining. For bulk symptoms or submucosal growths, minimally invasive procedures can help. Myomectomy removes fibroids while preserving the uterus. Uterine artery embolization shrinks them by reducing blood flow. We tailor choices, because the best option for a 28-year-old trying to conceive differs from that of a 45-year-old nearing menopause.
Adenomyosis: the hidden twin of endometriosis
Adenomyosis occurs when glandular tissue grows into the muscular wall of the uterus. The uterus often feels tender and enlarged. Symptoms include heavy periods, severe cramps, and pain that radiates to the back or thighs. It can mimic fibroids or coexist with them, which is why careful imaging matters. The NHS notes it is more common in women in their 40s and in those who have given birth. Ultrasound and MRI can show a thickened junctional zone and small cystic areas within the muscle.
Management focuses on bleeding control and pain relief. Hormonal IUDs are particularly helpful because they act inside the uterus. Oral or injectable progestins and combined pills also reduce bleeding and cramps. In resistant cases for those who have completed childbearing, hysterectomy offers a cure for adenomyosis-related pain and bleeding. We always balance relief with your reproductive goals.
Treatment pathways that balance relief and fertility
Good care aligns with what matters to you. Therefore, we frame decisions around three goals: control pain now, protect fertility when desired, and lower the chance of recurrence. Your Gynecologist will personalize the mix of medicines, lifestyle supports, and procedures.
- Reduce pain: NSAIDs, heat, pelvic floor therapy, and cycle-suppressing hormones.
- Control bleeding: levonorgestrel IUD, progestins, tranexamic acid, or combined pills.
- Remove disease or bulk: laparoscopic excision for endometriosis, myomectomy or hysteroscopy for fibroids, and definitive surgery when appropriate.
- Support fertility: time surgery with plans to conceive, and coordinate with a fertility team if needed.
Because lifestyle influences pain perception, we also discuss sleep, stress, and movement. Gentle exercise improves circulation and mood. Furthermore, tracking triggers helps you separate period pain from bowel or bladder causes. When fertility is a goal, we involve a reproductive specialist early to keep timelines realistic.
OB-GYN guidance on minimally invasive surgery
Many women worry that surgery will sideline their lives. In reality, modern hysteroscopy and laparoscopy usually mean smaller incisions, less pain, and faster return to daily tasks. For submucosal fibroids that distort the cavity, hysteroscopic resection through the cervix can dramatically cut bleeding. For endometriosis, laparoscopic excision removes implants while preserving healthy tissue. For adenomyosis, options include targeted adenomyomectomy in select cases or, for completed families, hysterectomy.
Recovery and risks in brief
Every operation carries risks such as bleeding, infection, or injury to nearby organs. Thankfully, these remain uncommon in experienced hands. We review them in detail before scheduling any procedure. After surgery, most patients walk the same day and resume light activity within a week, though individual recovery varies.
When to see a Gynecologist in Jaipur
If your pain is strong, cyclical, or paired with heavy bleeding, do not wait. Early evaluation prevents anemia, protects fertility, and reduces time lost to repeated flares. In our daily work at Surya Hospitals and Udbhav in Jaipur, we often help women who have lived with pain for years. Once they get a clear plan, daily life improves quickly. For compassionate, evidence-based care, you can consult Dr. Vibha Chaturvedi Sharma, or reach out via our trusted women’s health clinic in Jaipur.
Before your appointment, write your top three concerns. Additionally, bring previous scans and a simple symptom diary with dates, pain scores, and medicines tried. This short prep speeds diagnosis and makes the first visit more productive.
How we decide together
Shared decision-making sits at the center of great care. First, we match findings with your goals. Second, we explain trade‑offs in plain language. For example, some medicines ease pain but prevent ovulation while you take them. In contrast, surgery may offer longer relief but includes recovery time. Because of this, your plan may change over months as your needs evolve.
In our experience, small steps add up. For instance, a levonorgestrel IUD can lighten periods within weeks. Meanwhile, pelvic physiotherapy reduces spasms that worsen pain with sex. Then, if symptoms persist, we escalate to advanced imaging or laparoscopy at the right moment. This steady, staged approach prevents overtreatment yet moves you toward results.
Remember, information online guides but never replaces personal medical advice. Individual responses to treatment vary, and coexisting conditions can change choices. We follow recognized standards from bodies such as the American College of Obstetricians and Gynecologists and the Mayo Clinic to keep recommendations current and safe.
Key takeaways and a gentle next step
Persistent pelvic pain is not “normal,” even if it has been your normal for years. Endometriosis tends to cause cycle‑linked pain and can hide on scans. Fibroids often bring bulk symptoms and heavy bleeding. Adenomyosis usually makes the uterus tender and periods intense. With a careful history, targeted imaging, and, when needed, laparoscopy, we can reach a precise diagnosis and build a plan that fits your life.
If you live in or around Jaipur and need clarity, schedule a consultation. An experienced Gynecologist will assess your symptoms, explain options, and help you move forward at a pace that suits you. We aim for compassionate, evidence‑based care that respects your goals at every stage of life.
📞 Phone: 78499 09109
📍 SURYA HOSPITALS
C-8, B-7, Sawai Ram Singh Road,
Opposite SMS Hospital, Jaipur
📍 UDBHAV
A-35, Prince Road, Ajmer Road,
Vidhyut Nagar, Jaipur, Rajasthan – 302019
Book your consultation today for expert laparoscopic treatment and comprehensive women’s healthcare.